This guide explains how to build a telemedicine SaaS platform that serves many clinics from one codebase. You will learn the core features, multi-tenant architecture, HIPAA safeguards, 2026 regulatory rules, a phase-by-phase timeline, and realistic costs, starting at $3,000 for a proof of concept and $20,000 for a telemedicine MVP. It also shows two Technource healthcare platforms and the results they delivered.
Key Takeaways
A telemedicine SaaS platform must have HIPAA safeguards, tenant isolation, and video infrastructure designed into the architecture from week one. Retrofitting them later is the most expensive mistake teams make.
A telemedicine PoC starts at $3,000 and a clickable prototype at $6,000. A HIPAA-ready MVP costs $20,000 to $30,000 and takes 14–20 weeks. Multi-tenant SaaS platforms start at $30,000+, and enterprise builds are custom-quoted.
Compliance work typically accounts for 20–30% of total build cost. Each EHR integration adds 6–12 weeks, with cost based on the EHR vendor and read/write scope.
According to IBM report, healthcare breaches cost an average of $6.64 million in 2026. Technource’s Telepath platform achieved 65% faster e-prescribing approvals with a compliance-first SaaS build.
Telehealth is no longer a pandemic workaround. It is a permanent care channel, and investment is following it.
According to Grand View Research, the global telehealth market was valued at about $77 billion in 2025. It is projected to reach roughly $188 billion by 2033, growing at 11.5% a year.
North America holds about 45% of that market. U.S. policy also became more predictable in 2026, with Medicare telehealth coverage extended to the end of 2027.
The opportunity has shifted from single-clinic apps to platforms. Pharmacies, provider groups, and healthtech companies want to offer virtual care under their own brand, without building it themselves.
That is what a telemedicine SaaS platform does. But it is a regulated, multi-tenant product, not a video app with a calendar.
This guide takes a product engineering view. It covers what to build, how to architect it, how to stay HIPAA-ready, how long it takes, and what it costs.
What Is a Telemedicine SaaS Platform?
A telemedicine SaaS platform is cloud software that lets multiple healthcare organizations deliver virtual care under their own brand, on shared infrastructure, for a recurring subscription fee. Each organization, called a tenant, gets its own portal, providers, patients, and settings, while the vendor runs one codebase.
Building it is a product engineering problem as much as a healthcare one. The same multi-tenant patterns used in SaaS development apply here, with stricter rules on data access, audit, and isolation.
Telemedicine App vs Telemedicine SaaS Platform
A telemedicine app serves one practice, while a telemedicine SaaS platform serves many organizations from one product. The difference changes your architecture, compliance role, and revenue model.
Factor
Single Telemedicine App
Telemedicine SaaS Platform
Customers
One clinic or provider group
Many clinics, pharmacies, or health brands
Branding
One brand
White-label branding and custom domains per tenant
Five types of organizations build telemedicine SaaS platforms: digital health startups, pharmacy and direct-to-consumer brands, management services organizations, healthtech vendors, and health systems. Each one builds for a different reason, but they all need to serve multiple clinics or brands from one product.
Digital health startups selling virtual care software to clinics or specialty practices.
Pharmacy and direct-to-consumer brands that combine consults, prescriptions, and fulfillment.
Management services organizations (MSOs) running virtual care for many affiliated practices.
Healthtech vendors adding telehealth to an existing EHR, RPM, or practice management product.
Health systems offering a shared virtual care platform to partner hospitals.
Why Telemedicine SaaS Is a Strong Bet in 2026
Telemedicine SaaS is a strong bet in 2026 because reimbursement is stable through 2027, telehealth has settled into routine care, and buyers now prefer compliant platforms over building their own. Each of these trends also shapes what your product must support.
1. Reimbursement Is Stable Through 2027
The Consolidated Appropriations Act, 2026 extended key Medicare telehealth flexibilities through December 31, 2027.
These include home as the originating site, no geographic restrictions, and coverage for audio-only visits.
The law also requires CMS to create new telehealth billing modifiers by January 1, 2027.
Product Implication: keep billing codes and modifiers configurable, not hard-coded.
2. Telehealth Has Become Routine Care
About 3 in 10 U.S. adults used telemedicine in 2022, down from the pandemic peak (NCHS, via HealthDay).
That is not a decline. It is normalization. Patients now mix virtual and in-person visits.
Product implication: your platform must support hybrid care, follow-ups, and handoffs to in-person workflows, not just isolated video calls.
3. Compliance Is Now a Buying Criterion
Healthcare has had the highest data breach costs of any industry for 13 consecutive years, averaging $6.64 million per breach in 2026.
IBM also found 53% of breached organizations had not encrypted sensitive data at rest and in transit.
Product implication: expect security questionnaires in every enterprise sale. SOC 2 readiness and documented HIPAA controls shorten your sales cycle.
Custom Build vs White-Label Telehealth: Which Path Fits?
Build custom when virtual care is your core product or differentiator; use white-label when you need standard workflows live within weeks; choose a hybrid when you want to launch fast and move to owned IP later. The right choice depends on margin, control, and how unique your clinical workflow is.
Factor
Custom Build
White-Label
Hybrid
Time to launch
14–20 weeks (MVP)
Typically 4–10 weeks
4–10 weeks, then phased migration
Upfront cost
Starts from $20k
Low setup fee
Low first, custom spend later
Recurring cost
Hosting + maintenance
Per-provider or per-visit license
License until migration
Customization
Full control
Limited to vendor roadmap
Grows over time
IP ownership
100% yours
Vendor owns it
Yours after migration
SaaS margin
High at scale
Squeezed by license fees
Improves after migration
Best for
Specialty workflows, platforms you resell
Pilots, single-service clinics
Startups validating demand
Technource’s Recommendation: If you plan to sell the platform to other organizations, you need to own the code. Reselling a white-label product rarely leaves enough margin to build a SaaS business. If you’re still validating demand, understanding how to build an MVP can help you define the smallest version of the platform worth testing before expanding into a full multi-tenant saas product.
Core Features of a Telemedicine SaaS Platform
A telemedicine SaaS platform needs four feature groups: patient features, provider features, tenant admin features, and SaaS business features such as subscription billing and white-label branding. An MVP should ship the full patient-to-provider care loop first and defer advanced analytics and AI.
Patient Features
Patient features in a telemedicine SaaS platform cover the full path from sign-up to visit summary. In the table below, 8 of the 9 features belong in the MVP, and only visit summaries and records wait for V2.
Feature
What It Does
Phase
Registration and identity check
Account creation, ID verification, consent capture
MVP
Intake forms
Medical history, symptoms, insurance details before the visit
MVP
Scheduling and on-demand queue
Book a slot or join a live queue
MVP
Virtual waiting room
Device check and wait status before the provider joins
MVP
Video and audio visits
Encrypted consults with audio-only fallback
MVP
Secure messaging
Asynchronous chat with care team, file sharing
MVP
Prescriptions and pharmacy choice
Select pharmacy, track prescription status
MVP
Payments
Card payments, copays, subscriptions
MVP
Visit summaries and records
Care plans, notes, and documents after the visit
V2
Provider Features
Provider features give clinicians what they need to run a visit without switching tools, from the patient queue to e-prescribing. Six of the seven features below ship in the MVP, and lab orders and referrals follow in V2.
Feature
What It Does
Phase
Availability calendar
Shifts, time zones, and visit types
MVP
Patient queue and dashboard
Who is waiting, triage notes, priority
MVP
Video console with chart panel
See history and notes during the call
MVP
Clinical notes and templates
SOAP notes and specialty templates
MVP
E-prescribing
Send prescriptions electronically, including EPCS if approved
MVP
Licensure and state matching
Route patients only to providers licensed in their state
MVP
Lab orders and referrals
Order labs, share results, refer onward
V2
Tenant Admin Features
Tenant admin features let each clinic, pharmacy, or health brand manage its own portal without engineering help. The five areas below are branding, provider onboarding, service catalog, role-based access, and reports with audit logs.
Branding: logo, colors, content, and custom domain per organization.
Provider Onboarding: invite, credential, and assign providers to services.
Service Catalog: visit types, pricing, and intake forms per tenant.
Role-based Access: admin, provider, nurse, front desk, billing roles.
Reports and Audit logs: visit volume, revenue, and PHI access history.
SaaS Business Features
SaaS business features let the platform owner onboard tenants, charge for access, and support them safely. The five features below are tenant provisioning, subscription and usage billing, feature flags per plan, a super-admin console, and break-glass support access.
Tenant Provisioning: create a new organization in minutes, not weeks.
Subscription and Usage Billing: plans by provider seat, visit volume, or features.
Feature Flags per Plan: switch modules on or off by subscription tier.
Super-admin Console: platform health, tenant usage, and support tools.
Break-glass Support Access: time-limited, logged access for support staff.
Planning a telemedicine platform for multiple clinics?
A production telemedicine SaaS platform is built from seven layers: client apps, an API gateway, identity and tenancy, core clinical services, real-time communication, integrations, and a compliance-grade data and audit layer. All of it runs on HIPAA-eligible cloud services covered by a BAA.
1. The Seven Core Layers
A telemedicine SaaS platform runs on seven layers: client apps, API gateway, identity and tenancy, core services, real-time layer, integration layer, and data and audit layer. Each layer has one job, so you can scale or replace it without rebuilding the rest.
Layer
Responsibility
Typical Technology
Client apps
Patient app, provider app, admin web consoles
React / Next.js, React Native or Flutter
API gateway
Routing, rate limits, tenant resolution, WAF
AWS API Gateway, Kong, NGINX
Identity and tenancy
Login, MFA, roles, tenant context on every request
Keep services modular from the start. Scheduling, video, and billing scale differently, so you should be able to scale them independently.
2. Multi-Tenant Telehealth Platform Models
Telehealth SaaS platforms use one of three tenancy models: silo (separate stack per tenant), bridge (shared app with a separate database or schema per tenant), or pool (shared database with tenant IDs and row-level security). Understanding multi-tenant SaaS architecture helps you choose the right balance of isolation, cost, and scalability for your platform. Most platforms start with a pool or bridge for clinics and offer silo as an enterprise tier.
Model
Isolation
Cost per Tenant
Onboarding
Best Fit
Silo
Highest: dedicated stack
Highest
Days
Hospitals, health systems
Bridge
High: separate schema or DB
Medium
Minutes to hours
Mid-size provider groups
Pool
Logical: tenant ID + row-level security
Lowest
Minutes
Small clinics, solo practices
Engineering Rules that Prevent Tenant Data Leaks:
Four engineering rules prevent tenant data leaks in a multi-tenant telehealth platform: resolve the tenant at the gateway, enforce row-level security in the database, use per-tenant encryption keys for enterprise tenants, and test cross-tenant access on every release.
Resolve the tenant at the gateway and pass it in a signed token, never from a URL parameter alone.
Enforce row-level security in the database, not only in application code.
Use per-tenant encryption keys for enterprise tenants who ask for them.
Run automated tests that try to read another tenant’s data on every release.
3. Video Infrastructure
Most telemedicine platforms use WebRTC for real-time video, routed through a media server (SFU) or a managed video API whose vendor will sign a BAA. Managed APIs launch faster; self-hosted media servers cut per-minute cost at high volume.
Option
Pros
Cons
Best For
Managed video API (e.g., Twilio, Daily, Vonage, Agora)
Fast launch, global edge network, SDKs
Per-minute cost grows with volume; confirm BAA on your plan
MVPs and most SaaS platforms
Self-hosted SFU (e.g., LiveKit, mediasoup, Jitsi)
Lower unit cost, full control
You run TURN servers, scaling, and uptime
High-volume platforms
Deploy TURN servers so calls connect behind hospital firewalls.
Use adaptive bitrate and an audio-only fallback for weak networks. Medicare still covers many audio-only visits.
Keep recording off by default. When enabled, capture consent and encrypt recordings.
4. EHR Integration With FHIR and HL7
Telemedicine platforms connect to EHRs through FHIR R4 APIs for modern systems and HL7 v2 interfaces for older ones. Budget 6–12 weeks per EHR integration, with cost depending on the EHR vendor and whether you need read-only access or write-back.z
ONC’s Cures Act rule requires certified EHRs to offer standardized FHIR APIs, which makes read access more predictable.
Read-only access (demographics, allergies, medications) is the fastest path.
Write-back of notes and orders takes longer and needs clinical testing.
EHR app marketplace approvals often add weeks. Start them during discovery.
Integration engines can speed up multi-EHR support, at a recurring cost.
5. E-Prescribing, Pharmacy, and Payment Integrations
A telemedicine SaaS platform connects to four outside services: e-prescribing, pharmacy and shipping, payments, and notifications. Each one handles patient data differently, so each needs its own HIPAA rule.
E-prescribing: certified partners such as DoseSpot connect to pharmacy networks. Controlled substances need EPCS with identity proofing and two-factor signing.
Pharmacy Fulfillment: APIs route orders to partner pharmacies and shipping carriers.
Payments: many payment processors do not sign BAAs. Send only amounts and opaque IDs, never diagnoses or visit reasons.
Notifications: keep SMS, email, and push text PHI-free (“You have a new message”).
6. Tech Stack for a Telemedicine SaaS Platform: What Technource Recommends
Technource recommends React or Next.js for the web frontend, Node.js with NestJS for the backend, PostgreSQL with row-level security for data, and WebRTC for video, all on HIPAA-eligible cloud services under a signed BAA. For mobile apps, React Native or Flutter are strong cross-platform options, while Swift and Kotlin are better suited to device-heavy applications. This stack keeps hiring easy and tenant isolation enforceable at the database level.
Layer
Recommended Options
Web frontend
React.js or Next.js
Mobile apps
React Native or Flutter; Swift/Kotlin for device-heavy apps
Backend
Node.js / NestJS; Python for AI and data services
Database
PostgreSQL with row-level security; MongoDB for flexible clinical forms; Redis for queues
Video
WebRTC via managed API or self-hosted SFU
Cloud
AWS, Azure, or Google Cloud HIPAA-eligible services under a signed BAA
How to Build a HIPAA-Compliant Telemedicine Platform
A HIPAA-compliant telemedicine platform needs encryption in transit and at rest, MFA, role-based access, immutable audit logs, BAAs with every vendor that touches PHI, and a documented risk analysis. These controls must be built into the architecture, not added before launch.
If your platform creates, receives, stores, or transmits PHI for clinics, your company is a HIPAA business associate.
That means you sign a BAA with every tenant. You also need BAAs with your own subcontractors, such as cloud and video vendors.
Build a BAA template, a vendor inventory, and an incident response plan before your first tenant goes live.
2. Technical Safeguards to Build From Day One
A HIPAA compliant telemedicine platform needs nine technical safeguards built into the architecture from the first sprint, from encryption in transit and at rest to audit logging and data minimization. Adding them just before launch costs more and often means rework.
Safeguard
How to Implement It
Encryption in transit
TLS 1.2+ for APIs; DTLS-SRTP for WebRTC media
Encryption at rest
AES-256 via cloud KMS; per-tenant keys for enterprise tiers
Access control
Role-based access scoped to tenant, least privilege by default
Multi-factor authentication
Required for providers, admins, and support staff
Audit logging
Immutable log of every PHI read, write, export, and admin action
Automatic logoff
Session timeouts on shared clinical devices
Backup and recovery
Encrypted, tested backups with defined RPO and RTO
Cloud hosting, video API, e-prescribing, and AI vendors must all sign a BAA, while payment processors often will not. Check each vendor type in the table below before you commit to a contract.
Vendor Type
BAA Needed?
Practical Note
Cloud hosting
Yes
Use only HIPAA-eligible services listed in the provider’s BAA
Video API
Yes
Confirm BAA coverage on your specific plan
E-prescribing partner
Yes
Usually part of the onboarding contract
AI / LLM APIs
Yes
Use zero-retention or healthcare plans only
Email and SMS
Yes, if PHI is sent
Better: keep messages PHI-free
Analytics and error tracking
Yes, or strip PHI
Scrub PHI before events leave your system
Payment processor
Often unavailable
Send amounts and IDs only
4. Proposed HIPAA Security Rule Changes
HHS proposed the largest update to the HIPAA Security Rule in two decades in January 2025 (HHS).
It would make encryption and MFA mandatory, remove the “addressable” option, and require asset inventories, vulnerability scans, and annual compliance audits.
As of mid-2026, the rule is still proposed, with no confirmed final date.
Technource Recommendation: Build to the proposed rule now. These controls are already standard in enterprise security reviews, and retrofitting them later costs more.
5. Beyond HIPAA: Licensing, Prescribing, and Global Rules
A telemedicine SaaS platform also has to follow state licensure rules, DEA prescribing rules, and, for non-U.S. tenants, regional privacy laws like GDPR. The three areas below show what each one means for your product.
1. Interstate Licensure
Providers must be licensed in the state where the patient is located during the visit. The Interstate Medical Licensure Compact now covers more than 40 states, plus DC and Guam.
2. Controlled Substance Prescribing
DEA telemedicine flexibilities for controlled substances run through December 31, 2026. A permanent special registration framework was proposed but not finalized.
3. GDPR and Non-U.S. Markets
Selling in the UK, EU, Canada, or Australia adds GDPR, PIPEDA, or Privacy Act duties and often data residency rules. Plan region-specific deployments early if global tenants are on your roadmap.
How Technource Helped Telepath Achieve 65% Faster E-Prescribing Approvals With a Scalable SaaS Platform
Telepath, a scalable SaaS pharmacy platform for healthcare organizations that needed branded portals, e-prescriptions, medicine ordering, telehealth appointments, and multi-tenant organization management. Technource solved this by building a multi-tenant platform that allowed different organizations to operate independent branded pharmacy portals from a shared system.
The platform used a scalable architecture with custom subdomains, flexible onboarding, and automated cart abandonment workflows. The technology stack included React.js, AWS S3, DoseSpot, Agora, Carepoint & TransitionRx, Easypost, and Paytheory to support e-prescribing, telehealth, pharmacy coordination, shipping, and payments.
Measurable Result
65% faster e-prescribing approvals
90% more transparent onboarding through flexible flows
Customizable pharmacy setup for different healthcare organizations
Automated cart recovery workflows to help improve purchase conversions
Connected pharmacy and shipping workflows through Carepoint, TransitionRx, and Easypost integrations
How to Build a Telemedicine Platform: Step-by-Step Process
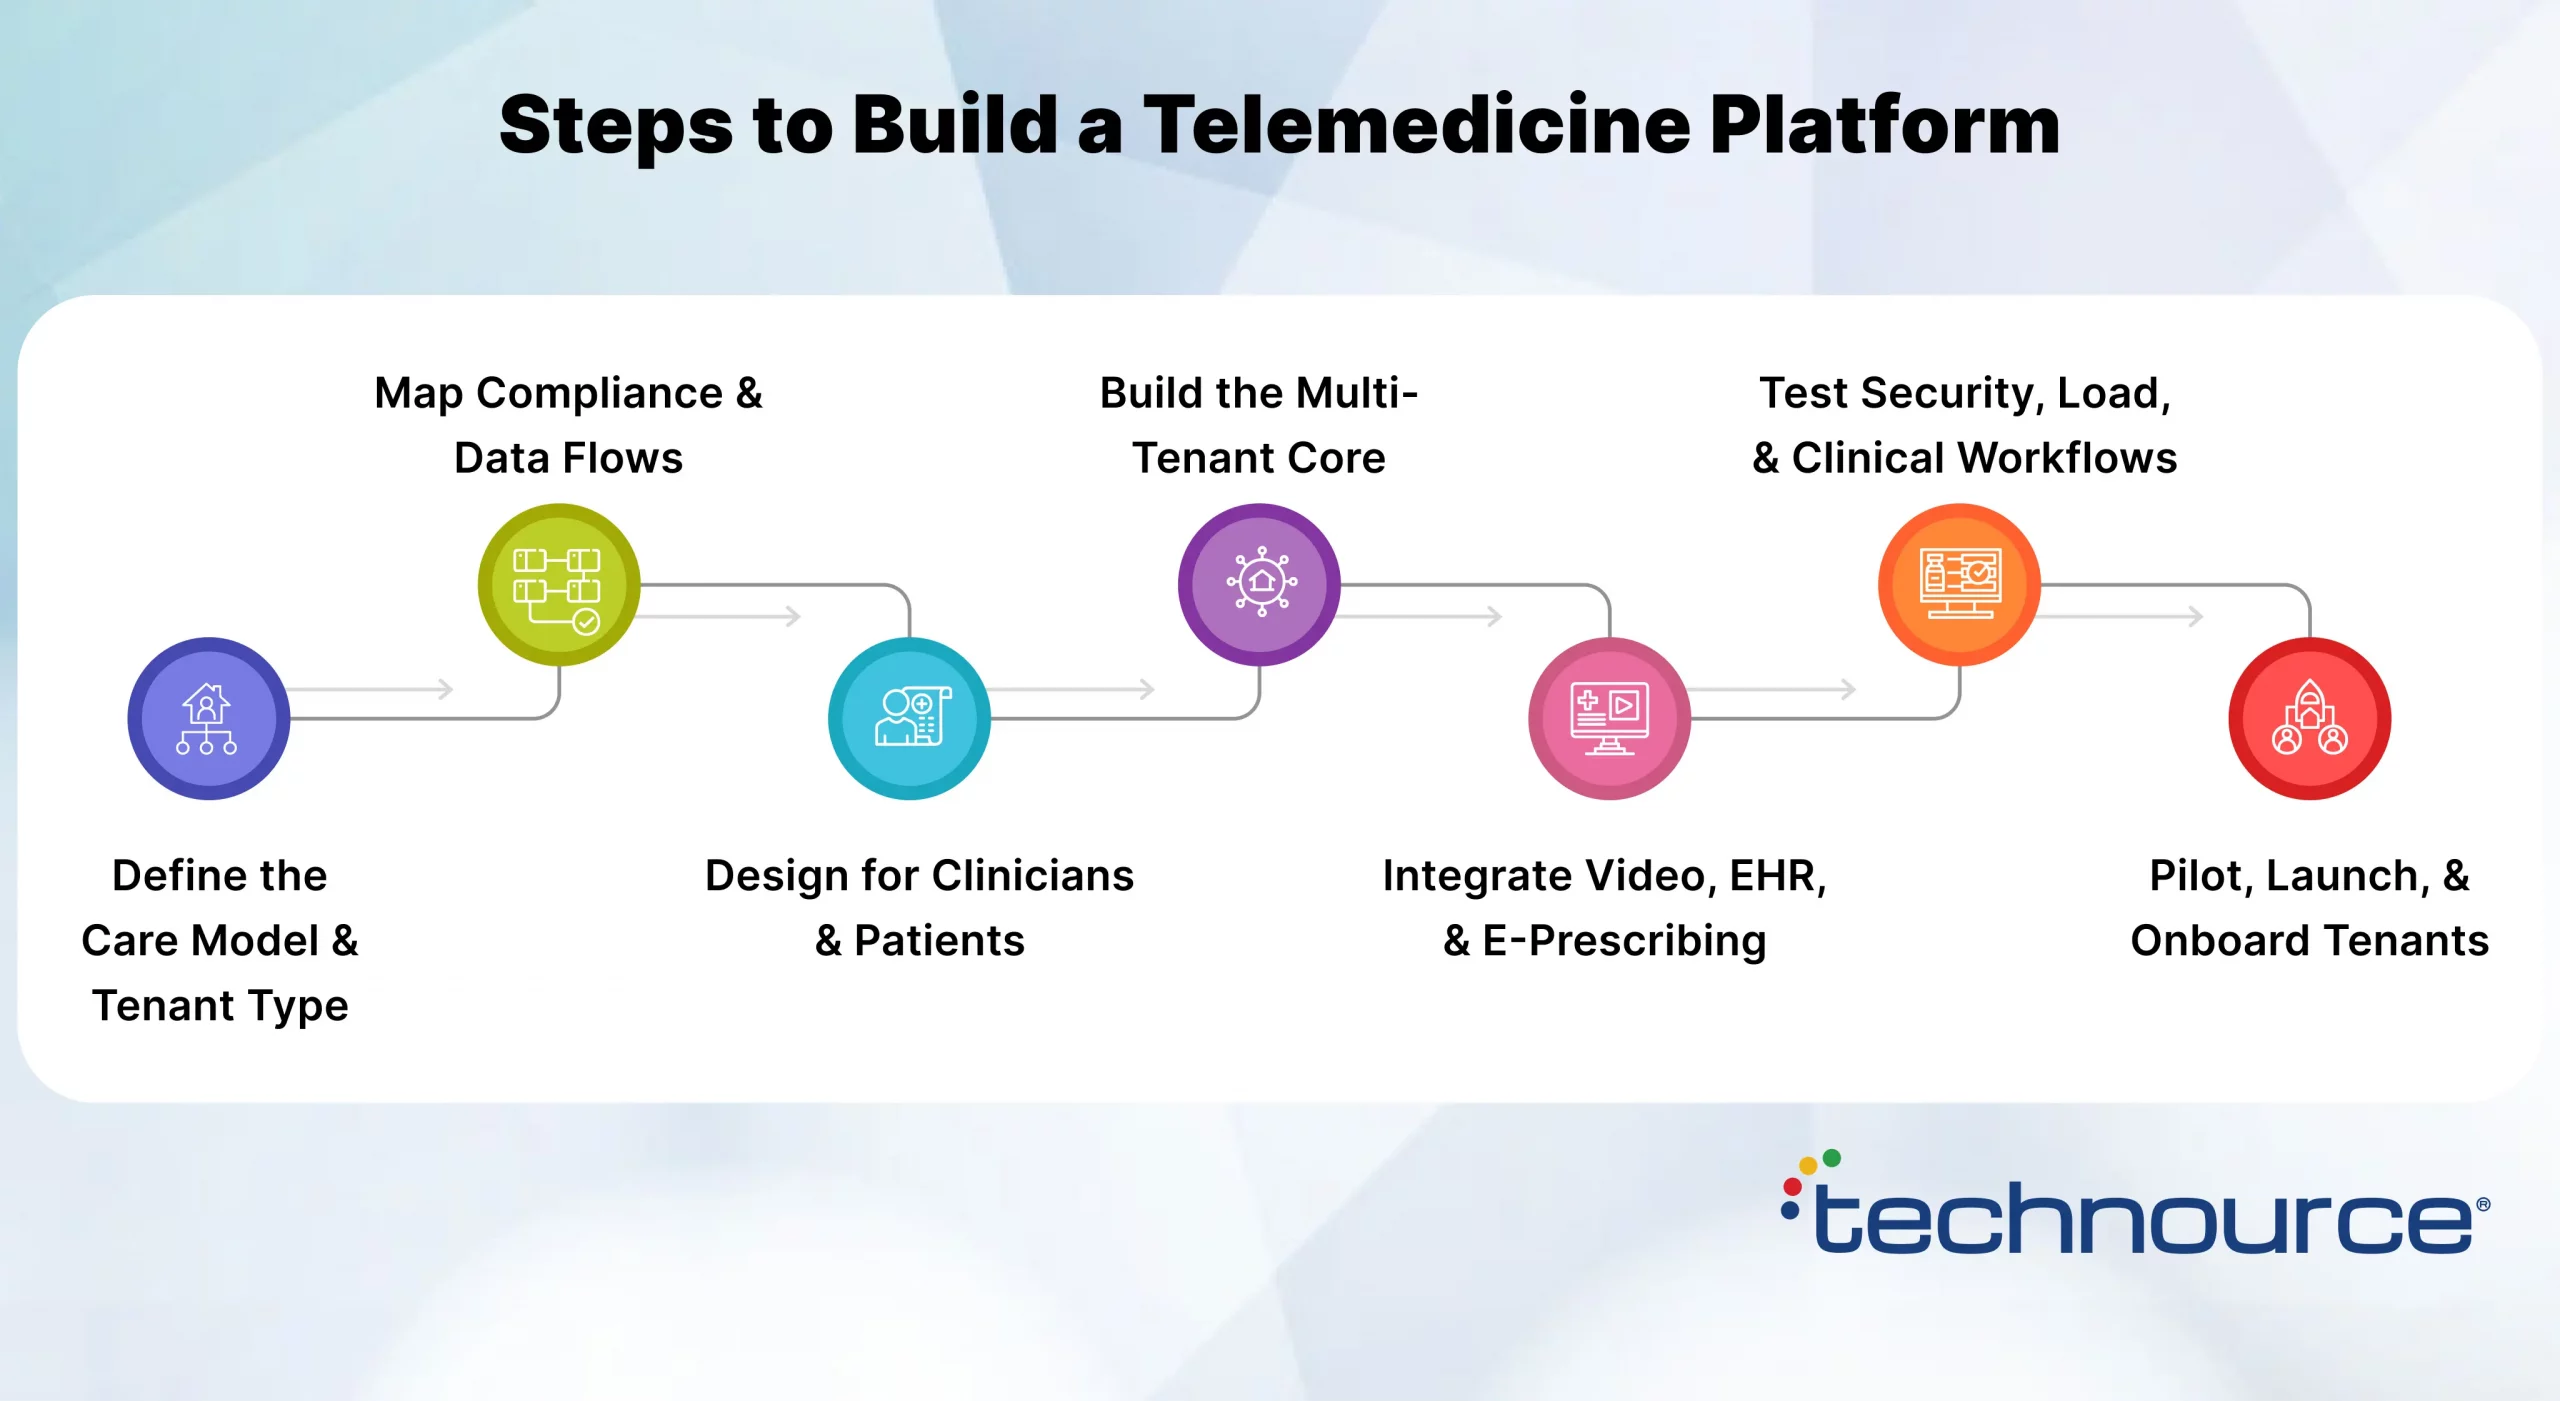
To build a telemedicine platform, define the care model, map compliance and data flows, design clinician-first UX, build the multi-tenant core, integrate video, EHR, and e-prescribing, test security and load, then pilot with one to three tenants before scaling. An MVP following these steps typically takes 14–20 weeks.
Decide what care you deliver: urgent care, behavioral health, chronic care, weight management, or pharmacy.
Then decide who pays: clinics, employers, patients, or payers.
Output: care model, tenant profile, and MVP scope.
Step 2: Map Compliance and Data Flows
Draw every place PHI is created, stored, and sent. List each vendor and confirm its BAA.
Run a HIPAA risk analysis on the design.
Output: data flow diagram, vendor list, risk register.
Step 3: Design for Clinicians and Patients
Clinicians judge a platform by clicks per visit. Patients judge it by how fast they reach a provider.
Test clickable prototypes with 3–5 real clinicians before coding.
Output: validated UX for patient, provider, and admin flows.
Step 4: Build the Multi-Tenant Core
Build identity, tenancy, roles, scheduling, and audit logging first. Every other feature depends on them.
Output: a secure core that new modules plug into.
Step 5: Integrate Video, EHR, and E-Prescribing
Start with one EHR and one e-prescribing partner. Add more only when tenants demand them.
Output: a working end-to-end visit, from booking to prescription.
Step 6: Test Security, Load, and Clinical Workflows
Run penetration tests, cross-tenant access tests, and load tests for peak hours.
Have clinicians complete real visit scenarios in staging.
Output: a signed-off, production-ready release.
Step 7: Pilot, Launch, and Onboard Tenants
Launch with one to three pilot tenants. Track visit completion rate, wait time, and video failure rate.
Fix friction, then open self-serve onboarding.
Output: a repeatable tenant onboarding playbook.
How Long Does It Take to Build a Telemedicine SaaS Platform?
A telemedicine MVP takes 14–20 weeks, a multi-tenant SaaS platform takes 5–8 months, and an enterprise platform with multiple EHR integrations takes 9–14 months. EHR approvals and BAA negotiations are the most common causes of delay. For teams looking to validate the core care workflow before investing in a larger platform, MVP development services can provide a focused starting point.
Phase
Duration
Key Output
Discovery and compliance architecture
2–4 weeks
Scope, data flows, risk analysis, architecture
UX/UI design and prototype
3–4 weeks (overlaps discovery)
Validated patient, provider, and admin flows
Core platform build
8–12 weeks
Identity, tenancy, scheduling, visits, notes
Integrations
4–8 weeks (runs in parallel)
Video, e-prescribing, payments, first EHR
Security testing and UAT
2–3 weeks
Pen test, load test, clinical sign-off
Pilot launch
2–4 weeks
First tenants live, feedback loop
The timeline by platform scope depends on how many tenants, EHR integrations, and compliance controls the first release must support. A telemedicine MVP takes 14 to 20 weeks, and an enterprise platform can take up to 14 months.
Platform Scope
Typical Timeline
Telemedicine MVP (single brand, core visit loop)
14–20 weeks
Multi-tenant SaaS platform (white-label, billing, one EHR)
What usually slows a build: EHR marketplace approvals, vendor BAA reviews, state-specific prescribing rules, and late scope changes from pilot clinics.
Want a realistic timeline for your telemedicine platform?
How Much Does It Cost to Build a Telemedicine SaaS Platform?
A telemedicine platform starts at $3,000 for a proof of concept, $6,000 for a prototype, and $20,000 – $30,000 for a HIPAA-ready MVP. Multi-tenant SaaS platforms start at $30,000+, and enterprise builds are custom-quoted. The biggest cost drivers are EHR integrations, tenancy and billing features, and compliance work.
Cost by Platform Scope
A telemedicine SaaS platform costs $20,000 to $30,000 for an MVP and $30,000+ for an enterprise build. Scope, mainly the number of EHR integrations and tenant features, decides where your project lands.
Scope
Cost Range
Timeline
What’s Included
Telemedicine MVP
$20k – $30K
14–20 weeks
Patient and provider apps, video, scheduling, messaging, e-Rx, payments
Multi-tenant SaaS platform
$30k+
5–8 months
MVP + white-label tenancy, subscription billing, admin consoles, one EHR
Plan for 15 to 20% of the initial build cost every year after launch, plus cloud hosting, video usage, licenses, and compliance. These costs recur, so they belong in your budget from day one.
Maintenance and Updates: 15–20% of the initial build cost per year.
Cloud Hosting: HIPAA-eligible services, backups, and monitoring.
Video Usage: Billed per participant-minute on managed APIs.
Compliance: Annual risk analysis, penetration test, and SOC 2 audit if required.
How to Reduce Cost Without Cutting Compliance
You can lower the build cost by launching with one EHR, a managed video API and cross-platform mobile apps, without removing any HIPAA safeguards. The six options below show where the savings come from.
Launch with one EHR and add others when tenants pay for them.
Use a managed video API first; move to self-hosted only at high volume.
Build mobile apps cross-platform unless you need deep device access.
Start with pool or bridge tenancy and sell silo as a premium tier.
Defer insurance claims if your first tenants are cash-pay.
Use AI-assisted engineering for test generation and documentation to shorten delivery.
How Do Telemedicine SaaS Platforms Make Money?
Telemedicine SaaS platforms usually charge tenants a monthly subscription per provider or per location, plus usage fees for visits or video minutes and one-time setup fees for white-label onboarding. Many combine two or more models.
Model
How It Works
Best For
Watch Out For
Per-provider seat
Monthly fee per active provider
Clinics and group practices
Inactive seats cause churn
Tiered plans
Feature bundles by plan
Mixed SMB and enterprise
Needs feature flags in code
Usage-based
Fee per visit or video minute
Variable-volume tenants
Revenue is less predictable
Setup fee
One-time onboarding and branding fee
White-label deployments
Can slow small-tenant sales
Revenue share
Percentage of visit or product revenue
Pharmacy and DTC platforms
Requires clean payment data
Product Implication: build metering into the architecture from day one. Retrofitting usage tracking is slow and error-prone.
How Technource Helped My Vital View Achieve 50% Faster Clinical Decision-Making With a Remote Care SaaS Platform
We built My Vital View, a B2B SaaS remote health monitoring platform for a U.S. healthcare organization offering remote patient monitoring (RPM) and chronic care management (CCM). The client needed one system to connect providers with patients at home, manage medical devices, and automate RPM and CCM workflows.
Technource built role-based dashboards for patients, providers, staff, clients, and admins, with device data synced via Bluetooth (BLE) and an IMEI-based BodyTrace API. We added a retest logic that asks patients to confirm extreme readings before alerting providers, plus automated session tracking for RPM and CCM billing. The stack included Node.js, React.js, React Native, MongoDB, Twilio, SendGrid, WestFax, and the BodyTrace API.
Measurable Result
50% faster clinical decision-making
100% remote access capability for patients and care teams
Fewer unnecessary provider alerts through automated retest logic
Automated RPM and CCM session tracking, monthly reports, and billing logs
Live on web, iOS, and Android with secure video calls and in-app messaging
Common Challenges in Telemedicine Platform Development
The most common challenges are unstable video on weak networks, low clinician adoption, tenant data isolation, slow EHR integrations, and sudden demand spikes. Each one has a known architecture or product fix.
The biggest telemedicine SaaS trends for 2026–2028 are AI-powered clinical documentation, AI-powered workflow automation for intake and triage, the merger of telehealth with remote patient monitoring, and hospital-at-home programs. Platforms that build for these now will win enterprise deals later.
AI-Powered Clinical Documentation
Ambient AI can draft visit notes from the consultation, which clinicians review and sign.
Build requirement: BAA with the AI vendor, zero data retention, and clear human approval before notes enter the record.
AI-Powered Workflow Automation
AI can automate intake summaries, visit routing, follow-up reminders, and prior authorization paperwork. AI automation services can support these workflows while keeping clinical decisions with clinicians.
Keep clinical decisions with clinicians. Software that diagnoses or recommends treatment may fall under FDA oversight.
Telehealth and RPM Convergence
Buyers want one platform for virtual visits and continuous monitoring. Connected devices turn one-off consults into ongoing care programs.
This is why device integration and alert logic now appear in enterprise RFPs.
Hospital-at-Home and Hybrid Care
The Acute Hospital Care at Home program has been extended through 2030.
Expect demand for platforms that coordinate video visits, devices, and in-person staff in one workflow.
Why Choose Technource to Build Your Telemedicine SaaS Platform
Technource is an AI-powered product engineering company. We design, build, and scale SaaS platforms, not one-off apps.
Product Engineering, Not Just Development
We help you shape the care model, tenancy strategy, and pricing model before writing code. That prevents expensive rebuilds after your first tenants go live.
Healthcare Platforms Already in Production
Our healthcare work includes Telepath (65% faster e-prescribing approvals) and My Vital View (50% faster clinical decision-making).
We have served 50+ healthcare clients across 14+ years and 1,000+ delivered projects.
Compliance-First Architecture
HIPAA safeguards, BAA-ready vendors, audit logging, and tenant isolation are part of our default architecture, not add-ons.
AI-Powered Delivery
We use AI across our engineering process for code review, test generation, and documentation. That shortens delivery without cutting quality.
Flexible Engagement Models
Fixed-cost project: clear scope and milestones for MVPs.
Dedicated team: long-term platform development and scaling.
Agile model: continuous feature delivery after launch.
Conclusion
A telemedicine SaaS platform is a regulated, multi-tenant product. Success depends on decisions made in the first few weeks.
Choose your tenancy model early. Design HIPAA safeguards into the architecture. Start with one EHR and one prescribing partner.
Plan for 14–20 weeks for an MVP and 5–8 months for a full multi-tenant platform. Validate with a PoC from $3,000, launch an MVP starting from $20,000+, and get multi-tenant and enterprise builds quoted by scope.
The market is growing, and Medicare coverage is stable through 2027. The window favors teams that launch a compliant, focused product and scale from real tenant feedback.
The right partner for SaaS product development services treats your platform as a long-term business solution, not a project. That means owning architecture, compliance, and outcomes together.
Planning a telemedicine SaaS platform for your clinics or pharmacy network?
A telemedicine MVP takes 14–20 weeks. A multi-tenant SaaS platform with white-label branding, subscription billing, and one EHR integration takes 5–8 months. Enterprise platforms with multiple EHRs, RPM, and AI features take 9–14 months. EHR marketplace approvals and vendor BAA reviews are the most common causes of delay.
A telemedicine PoC costs $3000 to $ 8,000, and a prototype costs $ 6,000 to $12,000. A HIPAA-ready MVP costs $20,000 to $30,000, and AI-powered MVPs range from $10,000 to $50,000+. Multi-tenant SaaS platforms start at $30,000+, and enterprise builds are custom-quoted. After launch, plan for 15–20% of build cost per year for maintenance. Compliance work makes up 20–30% of the build.
Yes. If your platform creates, receives, stores, or transmits PHI for healthcare providers, you are a business associate. You must sign a BAA with each tenant and get BAAs from your own vendors, such as cloud and video providers. Healthcare breaches averaged $6.64 million in 2026, so tenants will check this closely.
WebRTC is the standard for real-time video. Most platforms use a managed video API whose vendor signs a BAA on the chosen plan. Self-hosted SFU servers make sense at high volume. Either way, add TURN servers, adaptive bitrate, and an audio-only fallback, since Medicare covers many audio-only visits through December 31, 2027.
Use multi-tenant (pool or bridge) for small and mid-size clinics, because it keeps cost per tenant low and onboarding fast. Offer single-tenant (silo) deployments as a premium tier for hospitals and health systems. Multi-tenant platforms with white-label branding start at $30,000+, while single-tenant enterprise deployments are custom-quoted.
Yes. The Consolidated Appropriations Act, 2026 extended key Medicare telehealth flexibilities through December 31, 2027. Patients can receive covered telehealth at home in any location, and many audio-only visits remain covered. CMS must also introduce new telehealth billing modifiers by January 1, 2027.
Yes, for now. DEA flexibilities allow prescribing controlled substances via telemedicine without a prior in-person visit through December 31, 2026. A permanent special registration framework has been proposed but not finalized, so build prescribing rules as configurable policies you can update without a new release.
Use white-label if you need a standard service live in about 4–10 weeks. Build custom if you plan to resell the platform, need specialty workflows, or want to own your IP. A custom MVP takes 14–20 weeks but protects your SaaS margin.
Start with AI-powered workflow automation that saves clinician time: intake summaries, visit routing, follow-up reminders, and draft clinical notes. AI features typically cost 15,000–60,000. Use only AI vendors that sign a BAA and keep a clinician review step before anything enters the medical record.
Each EHR integration typically takes 6–12 weeks. Read-only FHIR R4 access is the fastest path. Writing notes and orders back to the chart takes longer, costs more, and needs clinical testing. Final cost depends on the EHR vendor and integration scope. Start EHR marketplace approvals during discovery to avoid delays.


 AI ConsultingStrategic AI Roadmaps